
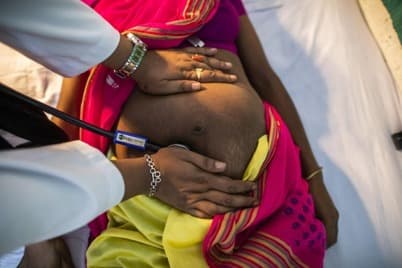
Accra, Ghana, October 5, 2026: Almost three Ghanaian women die every day from pregnancy and childbirth. Government recorded 986 maternal deaths in 2024 and 965 in 2025. Officials now call maternal mortality the only major health indicator still moving in the wrong direction, even after a decade of expanding access to skilled care.
That contradiction sits at the heart of Ghana's maternal health crisis. Women are reaching clinics and hospitals in growing numbers. Too often, the danger lies in what happens after they arrive, when speed, equipment and skill decide which complication becomes a death.
How bad is Ghana's maternal mortality crisis?
According to Deputy Health Minister Grace Ayensu-Danquah, Ghana's maternal mortality ratio stood at 235 deaths per 100,000 live births in 2024. That figure translates into 986 recorded deaths that year, and 965 in 2025.
Estimates vary by methodology. The 2017 Ghana Maternal Health Survey put the ratio at 310, and MPs have cited a figure closer to 300 in recent parliamentary debate. Every version places Ghana well above the UN Sustainable Development Goal target of 70 deaths per 100,000 live births by 2030, and roughly thirteen times the rate recorded in the United States.
The trend worries officials most. Parliamentary records show 430 maternal deaths in the first half of 2023, 437 in the first half of 2024, and 504 in the first half of 2025. Government has now made a 20% reduction in maternal deaths by December 2026 a presidential priority.
Why are Ghanaian women still dying despite high antenatal care attendance?
Ghana's antenatal coverage looks strong on paper; around 98% of women see a skilled provider during pregnancy, and 89% attend four or more antenatal visits.
Dr Ayensu-Danquah has publicly asked why women who attended eight or more antenatal visits are still dying in labour. She has told parliament's Economy and Development Committee that investigations show most women who died had already seen a health professional before losing their lives.
The answer lies less in whether women reach a clinic and more in what happens once they are inside it. Attendance measures contact with the health system. It does not measure whether that contact caught a danger sign in time, or whether the system could act on it fast enough.
What is actually killing pregnant women in Ghana?
Postpartum haemorrhage remains Ghana's leading cause of maternal death, followed by hypertensive disorders such as pre-eclampsia and eclampsia, then sepsis and obstructed labour. Hypertensive disorders alone have accounted for between roughly 19 and 37% of deaths depending on the period studied, and their share has reportedly doubled over the past decade.
Roughly six in ten maternal deaths happen after delivery, not during it. That single statistic reframes the crisis; the danger does not end when a woman gives birth, and neither should the care.
The three delays: why care doesn't arrive in time
Maternal health researchers studying Ghana often reach for a model called the three delays: delay in a family's decision to seek care, delay in reaching a facility, and delay in receiving adequate care once there.
The model explains a pattern that would otherwise look contradictory. A woman can attend every antenatal visit, reach a hospital in time, and still die if that hospital has no blood, no oxygen or no attendant able to manage her specific complication. Every argument Ghanaians make about this crisis, about CHPS compounds, about midwives, about caesarean sections, maps onto one of these three delays.
Where Ghana's maternal health system breaks down CHPS compounds: built for access, not equipped for emergencies
Community-based Health Planning and Services compounds bring antenatal care, delivery and postnatal checks to rural doorsteps. The complaint that many lack scanners and basic equipment is well documented, not anecdotal.
A study of CHPS use in the Yendi Municipality found compounds without reliable power or water, unable even to sterilise their own equipment, and short of the incentives needed to keep staff in post. Research in rural northern Ghana found emergency transport available at just one in fourteen facilities.
Government has started responding with targeted equipment drops, including a digital X-ray machine, an ultrasound scanner and new delivery beds for Kasoa Mother and Child Hospital this year. These remain one-off, facility-by-facility fixes rather than a national standard every CHPS compound can rely on.
Weak referral systems leave women stranded
Dr Ayensu-Danquah has identified two system-level bottlenecks driving the crisis; the failure to detect high-risk pregnancies early at the primary care level, and severely weak emergency referral systems. She has told frontline health workers that deaths could fall almost immediately if facilities referred high-risk cases before labour begins rather than after an emergency develops.
Distance itself can be the deciding factor in survival. A woman in the Northern Region faces a very different maternal health system from a woman in Accra, and that gap runs through every stage of care, from the nearest CHPS compound to the nearest blood bank.
Ghana's midwife staffing paradox
Ghana employs about 40,700 registered midwives. More than 14,000 additional trained midwives remain unemployed, according to the Ghana Registered Midwives Association and NARM Ghana.
That paradox says more about deployment and budget failures than about a workforce unwilling to work. Midwifery associations have called publicly for more specialised training in managing complications such as postpartum haemorrhage and pregnancy-induced hypertension, not for lighter workloads or fewer demands.
The midwife is not the whole system
Public complaints about negligent or nonchalant health workers deserve a direct answer, because Ghanaian research does document real cases of disrespectful and abusive intrapartum care. Some midwives interviewed in one study described hitting or blaming labouring women as somehow justified, a pattern researchers now study across the region as obstetric violence.
The same body of research complicates any simple story of negligence. Midwives report carrying a heavy psychological toll after every maternal death they witness, describing the aftermath as feeling like the whole world dropping on them. Overwork, poor remuneration and thin staffing shape the conditions in which disrespectful care takes root.
Blaming individual health workers lets the system off the hook. Government's own diagnosis, missed early risk detection and weak referral pathways, points to structural failure rather than individual malice, and midwifery associations have asked for training and staffing, not sympathy.
The C-section debate misses the bigger problem
Caesarean section alone does not explain Ghana's maternal mortality crisis. Its expansion without matching safety infrastructure is the real risk.
Ghana's CS rate has climbed from about 16% of deliveries in 2017 to around 20 to 21% today, roughly matching the global average. The rate splits sharply by region; Greater Accra records around 32% of deliveries by CS, against under 10% in the Northern Region, the same urban-rural divide that shapes every other part of this crisis.
Ghanaian hospital data shows women who deliver by CS face a higher maternal mortality rate than those who deliver vaginally, about 36 deaths per 100,000 procedures against 9 per 100,000 for vaginal birth in one study. CS remains major abdominal surgery, carrying its own risk of bleeding and infection wherever blood banks, anaesthetists and post-operative monitoring run thin. The %debate should not ask whether caesarean section is dangerous. It should ask whether Ghana can guarantee the safety net around every caesarean it performs.
What government is doing to reduce maternal deaths
The Ministry of Health is finalising a Reproductive, Maternal, Newborn, Child, Adolescent Health and Nutrition Strategic Plan for 2026 to 2030, alongside a National Maternal Mortality Action Response Plan meant to standardise care and enforce quality assurance nationally.
Working with UNFPA, government has launched PRIMA, the Presidential Response to Maternal Emergency Response, reflecting the crisis's new status as a presidential priority. One intervention directly targets the leading cause of death: government is working to make heat-stable carbetocin, a drug that controls postpartum bleeding, available at roughly GH₵9 per dose instead of GH₵500 for the cold-chain version currently in use.
What has to change
The evidence points to one priority above all others. Getting more women into antenatal care will not, by itself, close this gap. Ghana needs a system that can identify danger early, stabilise a patient fast, and move her to the right level of care without delay, at every facility, not just the well-resourced ones.
That priority translates into specific measures. Equip every CHPS compound to the standard its own guidelines already set, rather than through one-off facility visits. Strengthen emergency referral and transport in rural districts, where distance itself often decides who survives. Deploy the thousands of trained, unemployed midwives already available, and give them the specialised skills to manage haemorrhage and hypertensive emergencies.
Enforce trauma-informed, respectful maternity care standards alongside that clinical training, since disrespectful care is a system failure as much as an individual one. Keep caesarean section available wherever it is medically necessary, while auditing what drives elective procedures in well-resourced urban facilities. Guarantee blood, heat-stable carbetocin and oxygen at every delivery point in the country, so survival stops depending on which facility a woman happens to reach.
Ghana doesn't lack the knowledge. It has a delivery problem.
Haemorrhage, hypertensive disorders, sepsis and obstructed labour are preventable or treatable with interventions the world has understood for decades. Ghana is not short of knowledge, and its health workers are not short of will.
What persists is the gap between what is known to work and what reaches women in time, especially rural, poorer women, in the hours that matter most. Closing that gap will not require a medical breakthrough. It requires the equipment, the staff and the systems to arrive consistently enough that pregnancy stops being a gamble for Ghanaian women.



